Lesson Ninety- two Arrhythmia- induced cardiomyopathy
2019-12-10童鸿
Tachycardia-induced Cardiomyopathy
Tachycardia-induced cardiomyopathy(T-CM)refers to the presence of a reversible LV dysfunction solely due to increase in ventricular rates, regardless of tachycardia origin. The risk of developing T-CM depends not only on the type, but also the duration and rate of tachycardia. A study reported T-CM in 2.7%patients referred for radiofrequency ablation(RFA);however,it also included patients referred for premature ventricular contractions ablation. T-CM has been reported in 10% of patients with atrial tachycardia(AT), and as high as 37% of patients with incessant AT. Moreover, permanent junctional reciprocating tachycardia appears to have the highest association with T-CM(20% to 50%)as it frequently presents as an incessant supraventricular tachycardia.
Pathophysiology and Mechanism
Animal models have been key to understand the pathophysiology and mechanism of T-CM. Similar to humans,animals exposed to persistent tachycardia using a continuous rapid atrial or ventricular pacing develop heart failure (HF)symptoms, left ventricular(LV)systolic dysfunction and dilatation, decrease in LV dP/dtmax and myocardial blood flow,and increase in LV wall stress and end-diastolic pressure and volume.Dilatation tends to be biventricular with mild thinning or no associated hypertrophy or change in heart mass. The progression of these physiological changes include a decrease in systemic blood pressure and increase in LV and pulmonary artery pressure, which plateaus at 1 week, while cardiac output, ejection fraction, and volumes continue to deteriorate the following 4 weeks with development of symptomatic HF within 2 to 3 weeks.
T-CM is characterized by structural and functional myocardial changes. Similar to human studies, T-CM models have also demonstrated electrical remodeling and abnormal Ca homeostasis thought to be responsible for impaired excitation-contraction coupling and diastolic dysfunction. Only total Ca cycling, Ca channel inhibition,and basal ATPase activity have demonstrated a statistical correlation with decrease in left ventricular ejection fraction(LVEF).
Clinical Presentation, Diagnosisi, and Imaging Features
Clinical studies have found a variable time from onset of arrhythmia symptoms to development of T-CM,ranging from 3 to 120 days with an overall LVEF of 32%. Regardless of tachyarrhythmia, HF symptoms will manifest earlier at higher tachycardia rates, such as patients with persistent atrial flutter or tachycardia with 2:1 AV conduction with rates >150 beats/min.A recent clinical study found a more severe LV dysfunction(LVEF 29.3±6.6%)in T-CM when compared with dilated and inflammatory CM (32.1±10.2% and 41.9±12.9%,respectively;P<0.001)
Major reported symptoms include palpitations(29%), HF class Ⅲto Ⅳ(47%), and syncope/presyncope(12%), while the remaining may have no symptoms. Sudden cardiac death is uncommon but has been reported in up to 8%to 12%despite treatment and resolution of cardiomyopathy.
Echocardiogram or cardiac magnetic resonance can assist in excluding other etiologies. T-CM is characterized by a dilated CM (increased LV end-diastolic dimension and area)with moderate to severe biventricular systolic dysfunction and normal LV septal and posterior wall thickness (lack of hypertrophy). Mitral insufficiency may be present due to LV and mitral annular dilatation with lack of leaflet coaptation.
Treatment
A major feature of T-CM is its reversibility once tachycardia is eliminated. Thus, the mainstay treatment consists of suppression of tachycardia based on the culprit arrhythmia1with antiarrhythmic drugs(AADs)and/or RFA.
Elimination of tachyarrhythmia not only resolves LV function within 4 to 12 weeks, but also improves heart failure symptoms by at least 1 New York Heart Association functional class in most patients.Unfortunately, the recovery of T-CM is not always complete. Histopathological abnormalities, diastolic dysfunction, and ventricular dilatation with a hypertrophic response may persist despite normalization of LVEF.
Prnmature Ventricular Contraction-Cardiomyopathy
Premature ventricular contractions-cardiomyopathy(PVC-CM)is defined as the development of LV dysfunction caused solely by frequent PVCs. A PVC burden≥10% is often considered high and significant enough to trigger PVC-CM.The prevalence of PVC-CM has been reported at 7% among patients with frequent PVC burden >10%. Clinical studies have reported a diagnosis of PVC-CM in 9%to 30%of patients referred for RFA of PVC.
Potential Mechanism(s)of PVC-CM
The primary cause of contractile dysfunction in PVC-CM appears to be disorders of the calcium-induced calcium release mechanism itself,with alterations of dyad(L-type Ca channel and Ryanodine receptor)function proposed as a potential mechanism.Similar to other cardiomyopathies, this PVC-CM model has revealed electrophysiological remodeling.Histopathological abnormalities are distinct without evidence of increased inflammation or apoptosis and minimal or no fibrosis. Mitochondrial studies have demonstrated no changes in oxidative phosphorylation.These findings are supported clinically by the lack of scar on cardiac magnetic resonance imaging of patients with PVC-CM.These findings further confirm a primary functional abnormality as a primary mechanism of this reversible CM. Whether all the cellular and molecular changes are in response to the CM rather than the cause of the CM remains unclear.
Predictors of PVC-CM
PVC burden has been shown to be a major predictor of PVC-CM. Two main studies have shown that PVC burden >16% and 24% best identifies patients with a diagnosis of PVC-CM. Although these and other studies suggest that a PVC burden of at least 10% is required to induce PVC-CM, other studies question this minimal PVC threshold,because they have shown improvement in LV function with PVC burden as low as 6% to 8% . The length of ambulatory ECG monitoring has important implications, because increasing the duration from a 24-h to a 7-day ambulatory Holter monitor can doubled the number of patients who reach the 10%threshold.
Some other PVC features have been found to be independent predictors for PVC-CM such as male sex,lack of symptoms or duration of palpitations >30 months, variability of PVC coupling interval, QRS duration of PVC >150 ms, and epicardial origin.PVC-CM index2, including PVC burden, PVC-QRS width, and epicardial origin, has been developed in an attempt to identify patients with high probability of PVC-CM.
Clinical Presentation, Diagnosis, and Imaging Features
The time course for the development of PVC-CM is unclear, but it is estimated to occur within months up to several years. Although animal studies with persistent high PVC burden(33% to 50%)develop CM within 4 weeks, human studies are not consistent in part due to the unclear onset and variability of PVCs.
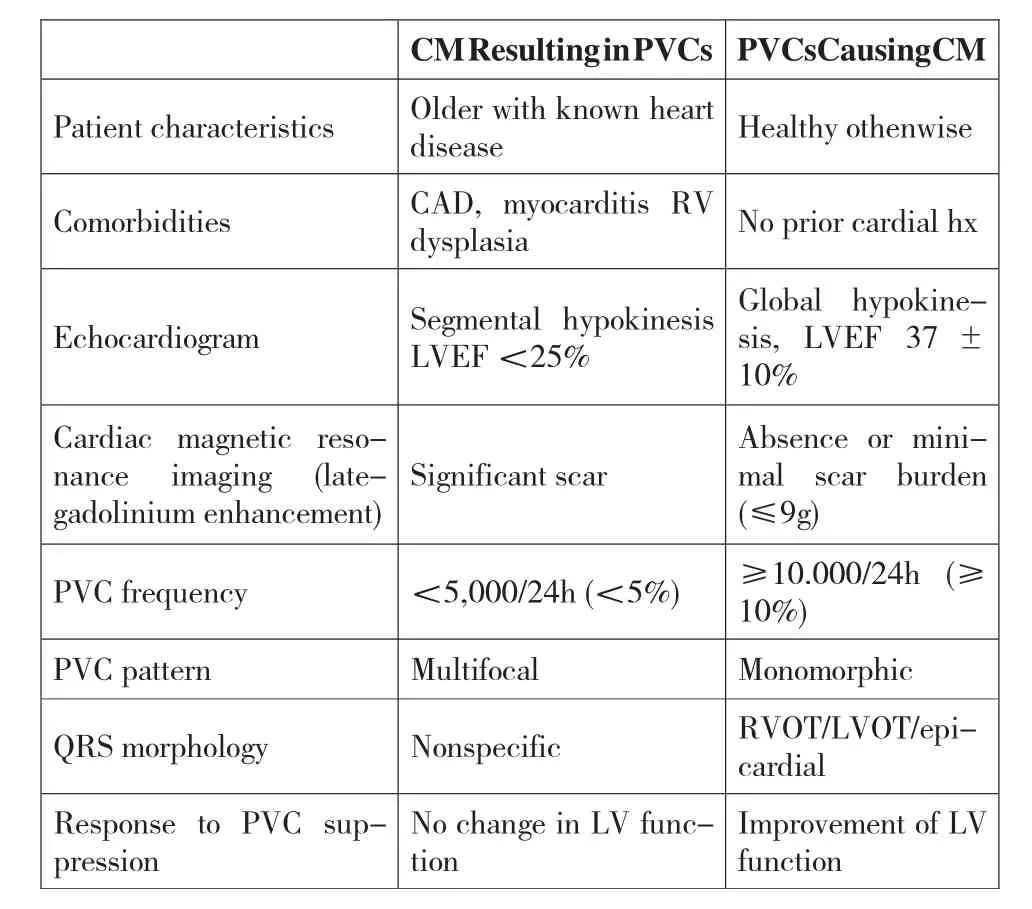
Table 1 Clinical and PVC Features to Identify PVC-CM
PVC-CM may have a wide range of presentations,from asymptomatic or vague symptomatology to heart failure and even syncope. It is unclear why some patients have symptoms related to PVCs while others do not, but a PVC coupling interval ratio <0.5 (PVC CI ratio: PVC coupling interval/Sinus coupling interval)has been proposed as an important marker of symptoms.
PVC-CM is a diagnosis of exclusion, to be suspected in patients with frequent PVCs >10% ,especially in nonischemic CM.A challenge is to identify when PVCs are the etiology of a CM or just "innocent bystanders" in patients with CM. Even if PVCs are the result of CM, these PVCs, if frequent, may contribute to and further worsen CM and HF symptoms; this is referred to as "superimposed" PVC-CM. In selected cases, echocardiographic and PVC features can help identify these patients (Table 1). PVC-CM is characterized by mild to moderate LV systolic dysfunction,LV dilatation,mild mitral regurgitation,and LA enlargement, which resolved within 2 to 12 weeks after elimination of PVCs. Cardiac imaging is key to identify LV dysfunction and prompt suspicion of PVC-CM in patients with high PVC burden(≥10%)(Table 1). Cardiac magnetic resonance with lategadolinium enhancement has the advantage of identifying scar and quantifying scar burden, which in turn potentially predicts the response to PVC suppression.
Treatment
Currently,a PVC suppression strategy with RFA or AADs is a widely accepted intervention to treat a CM that might be caused or exacerbated by frequent PVCs.However, the treatment of frequent PVCs(≥10%burden)without LV dysfunction (LVEF ≥50%),symptoms, or idiopathic ventricular fibrillation is less clear. PVC suppression is considered successful if burden is decreased by >80% of baseline PVCs, as it likely represents a true effect of treatment rather than spontaneous PVC variability.
PVC suppression in PVC-CM has been shown to improve LV function,LV dilatation,mitral regurgitation,and BNP levels. The mean improvement of LVEF after RFA in most studies is between 10% and 15% even in superimposed PVC-CM. A prospective study demonstrated a significant decrease in BNP levels while primary prophylaxis ICD implantation was avoided in 80% of all patients with PVC burden >13% due to significant improvement of LVEF after successful RFA.Another study found that 81%of patients with abnormal baseline estimated glomerular filtration rate had significant improvement in renal function after RFA of PVCs.
词 汇
Pathophysiology n.病理生理学
leaflet n.&v.瓣叶,散页印刷品,传单,小册子;散发传单
coaptation n.对合,接合,适应
histopathological adj.组织病理学的
apoptosis n.细胞凋亡,程序性细胞死亡
mitochondrial adj.线粒体的
oxidative adj.氧化的,具有氧化特性的
phosphorylation n.磷酸化
implication n. 含意,暗指,牵连,牵涉
vague adj.模糊的,微小的,不明确的,不具体的
symptomatology n. 症状学,症候学
innocent adj.无辜的,清白的,无罪的,无辜受害的;n.无辜者,单纯的人
superimpose v.叠加,叠映,使重叠
注 释
1.culprit arrhythmia 本文中指导致心肌病的心律失常,culprit在冠心病心肌梗死介入治疗中常译作“罪犯”,在此可译作“致病”,即致病心律失常。
2.PVC-CM index 指PVC-CM 指数,由PVC 负荷(0-1)×PVC-QRS 宽度(毫秒)×常数C(结构性心脏疾病为1.28,心电图提示心外膜起源为2)计算所得,≥39 分预测发生心肌病的风险高。
参考译文
第92 课 心律失常所致心肌病心动过速所致心肌病
心动过速所致心肌病(T-CM)是指因心室率加快而引起的可逆性左心室功能不全,不考虑心动过速的起源。发生T-CM 的风险不但取决于心动过速的类型,也取决于心动过速的频率和持续时间。有报道T-CM 占射频消融患者的2.7%。不过,这包含行室性期前收缩消融的患者。据报道10%的房性心动过速患者发生T-CM,这在顽固性房性心动过速患者高达37%。此外,持续性结性折返型心动过速因其常为顽固性室上性心动过速,T-CM 的发生率最高(20%~50%)。
病理生理与机制
动物模型是了解T-CM 病理生理和机制的关键。与人类相似,连续心房或心室起搏引起的持续性心动过速可诱发动物心力衰竭症状、左心室收缩功能不全和扩张,降低左心室dP/dtmax 和心肌血流,增加左心室室壁张力、舒张末压力和容量。……
