临床药师优化1例CRRT脓毒症休克患者行抗感染治疗的病例分析
2020-03-23李伟华范国荣高岸
李伟华 范国荣 高岸
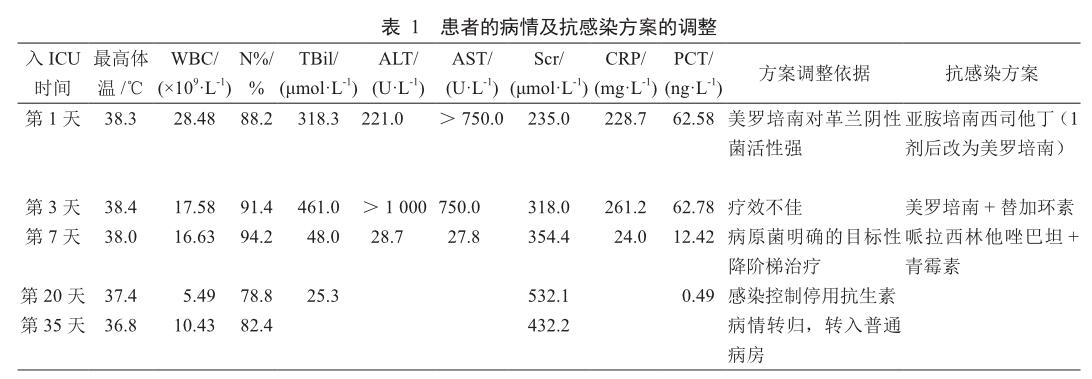
摘 要 目的:探讨连续性肾脏替代疗法(continuous renal replacement therapy, CRRT)治疗脓毒症休克患者的抗菌药物给药方法及临床药师在参与药物治疗中的作用。方法:临床药师参与1例术后混合细菌感染致脓毒症休克并行床边CRRT的患者抗感染治疗的全过程,基于病原菌的药敏结果、抗菌药物特性、CRRT对药物的清除以及脓毒性休克病理生理的改变,分析抗菌药物的品种选择及美罗培南初始给药剂量、给药方式的调整。结果:患者感染得到控制,未发生明显的不良反应。结论:在CRRT所致脓毒症休克患者治疗中,临床药师发挥专业优势,可协助医师优化抗感染治疗方案,提高临床疗效。
关键词 混合细菌感染 脓毒症休克 连续肾脏替代疗法 美罗培南延长输注 联合用药
中图分类号:R631.2; R969.3 文献标志码:C 文章编号:1006-1533(2020)03-0060-05
Analysis of a case of CRRT patient with septic shock undergoing anti-infective therapy by clinical pharmacists*
LI Weihua1,2**, FAN Guorong1, GAO An1***(1. Department of Clinical Pharmacy, Shanghai General Hospital, Shanghai Jiao Tong University, Shanghai 200080, China; 2. Department of Pharmacy, Xian Daxing Hospital, Xian 710000, China)
ABSTRACT Objective: To explore the efficacy of antibacterial drug regimen in a CRRT patient with septic shock and the role of clinical pharmacists in participating in medication. Methods: Clinical pharmacists participated in the whole process of anti-infective treatment of a patient with postoperative mixed bacterial infection and septic shock combined with bedside continuous renal replacement therapy (CRRT) and the selection of antibiotics and the adjustment of the initial dose and mode of administration of meropenem were conducted based on the susceptibility results of pathogens, antibacterial properties, and drug clearance by CRRT as well as the pathophysiological changes of septic shock. Results: The patients infection was controlled and no obvious adverse reactions occurred. Conclusion: Clinical pharmacists can play a professional advantage to assist physicians in optimizing anti-infective treatment programs and improving clinical efficacy in the treatment of patients with septic shock caused by CRRT.
KEY WORDS mixed bacterial infection; septic shock; continuous renal replacement therapy (CRRT); meropenem prolonged infusion; drug combination
膿毒症是指因感染引起的宿主反应失调导致的危及生命的器官功能障碍,在脓毒症基础上出现严重的循环障碍以及细胞和代谢的紊乱即为脓毒症休克[1],通常病死率较高,而急性肾损伤(acute kidney injury, AKI)又是导致脓毒血症死亡率升高的独立危险因素,因此,必要时临床上会采取连续性肾脏替代疗法(continuous renal replacement therapy, CRRT)。同时,对危及生命的感染采取早期恰当的抗菌药物治疗也非常关键。然而,脓毒症休克患者的病理生理学改变和CRRT的应用均会对抗菌药物的药代动力学特点产生影响。本文通过ICU临床药师参与1例脓毒症休克合并AKI的患者行CRRT过程中抗菌药物的选择及剂量调整,为临床合理使用提供参考。……
