能谱CTA评估脑分水岭梗死患者颅内外血管狭窄闭塞及侧支循环建立情况分析
2021-07-01梁文俊孙玙陈淦杨水泉黄州
梁文俊 孙玙 陈淦 杨水泉 黄州

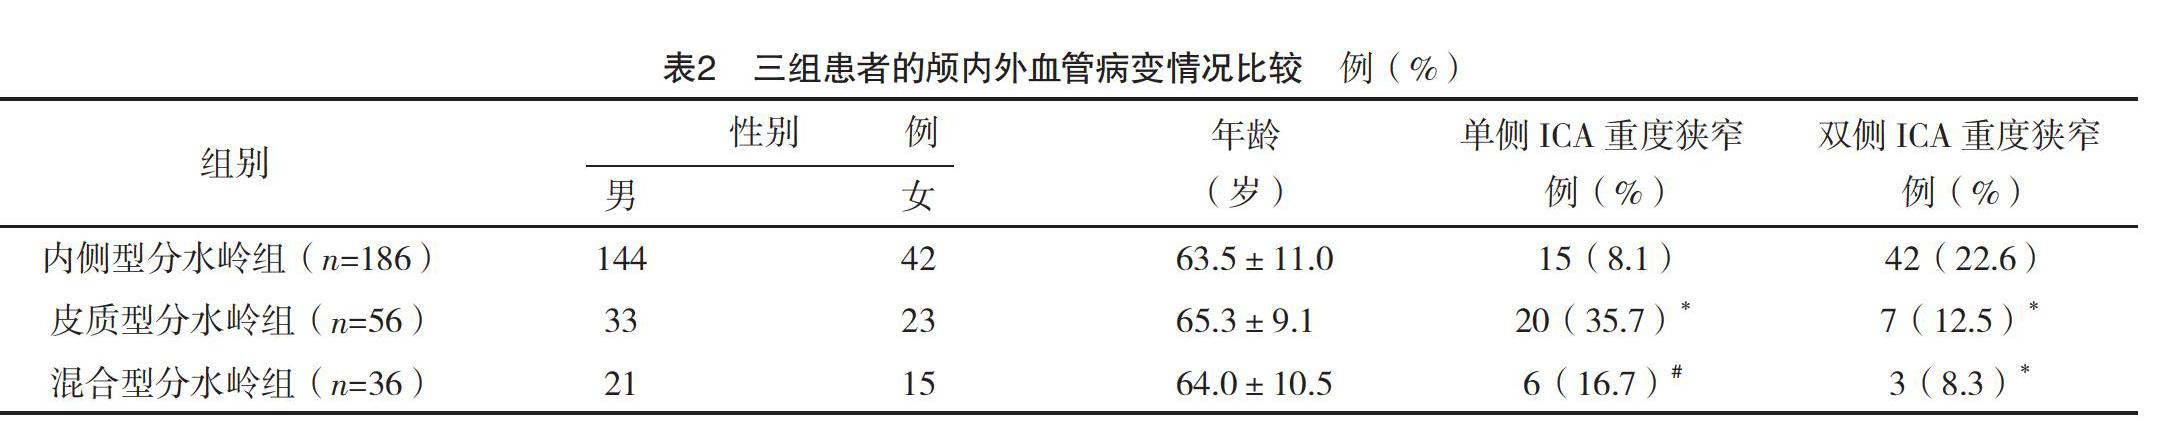
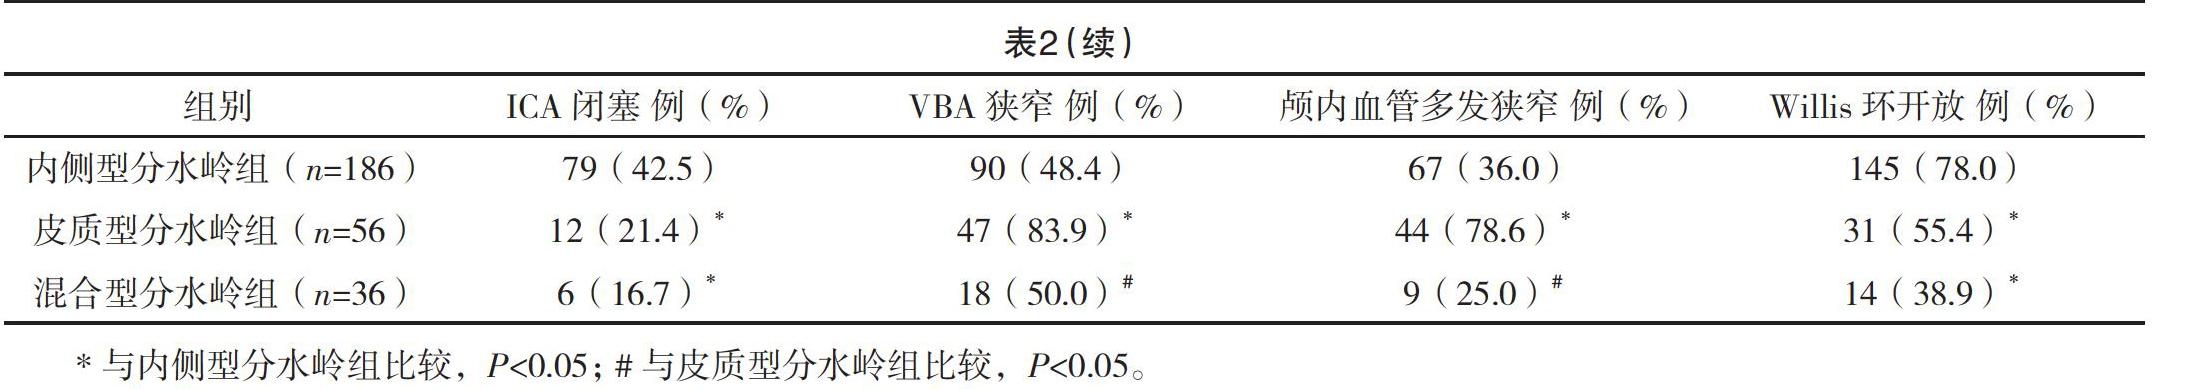
【摘要】 目的:探討能谱CTA评估脑分水岭梗死患者颅内外血管狭窄闭塞及侧支循环建立情况。方法:选取2019年1月-2020年3月因疑似脑分水岭梗死来本院接受治疗的400例患者为研究对象,依据数字减影血管造影(digital subtraction angiography,DSA)检查是否存在脑分水岭梗死将其分为脑分水岭梗死组(278例)与非脑分水岭梗死组(122例)。所有患者均进行能谱CTA检测,比较其血管病变与侧支代偿的相关情况。结果:脑分水岭梗死组ICA重度闭塞、狭窄以及颅内血管多发狭窄发生率均高于非脑分水岭梗死组,差异均有统计学意义(P<0.05)。内侧型分水岭梗死组双侧ICA重度狭窄、ICA闭塞及Willis环开放发生率均高于皮质型及混合型分水岭梗死组(P<0.05);皮质型分水岭梗死组单侧ICA重度狭窄、VBA狭窄以及颅内血管多发狭窄的发生率均高于内侧型及混合型分水岭梗死组(P<0.05)。278例患者中,190例Willis环开放,其中,66例单纯前交通开放、32例单纯后交通开放、52例前后交通同时开放、40例前后交通未开放。不同Willis环开放情况患者的梗死类型比较,差异均无统计学意义(P>0.05)。278例患者中,120例颅内血管多发狭窄,其中,34例软脑膜侧支代偿较差,86例软脑膜侧支代偿较好。软脑膜代偿较差患者皮质型脑分水岭梗死的发生率高于代偿较好患者,而内侧型及混合型脑分水岭梗死的发生率均低于代偿较好患者(P<0.05)。结论:脑分水岭梗死与患者颅内外血管狭窄、闭塞情况紧密相关,前交通动脉的存在能够促使内侧型脑分水岭梗死患者的发生率显著降低;大脑中动脉病变时软脑膜代偿情况的出现能够促使受累皮质血供情况增加,软脑膜侧支代偿较差者极易导致皮质型脑分水岭梗死情况的发生,通过能谱CTA检测对患者具体情况进行准确评估,有助于采取针对性的预防及治疗措施。
【关键词】 能谱CTA 脑分水岭梗死 颅内外血管 狭窄 闭塞 侧支循环
Energy Spectrum CTA Assessment of Intracranial and Extracranial Vascular Stenosis Occlusion and Collateral Circulation Establishment in Patients with Cerebral Watershed Infarction/LIANG Wenjun, SUN Yu, CHEN Gan, YANG Shuiquan, HUANG Zhou. //Medical Innovation of China, 2021, 18(13): -150
[Abstract] Objective: To evaluate the intracranial and extracranial vascular stenosis and occlusion and the establishment of collateral circulation in patients with cerebral watershed infarction by energy spectrum CTA. Method: A total of 400 patients with suspected cerebral watershed infarction in our hospital from January 2019 to March 2020 were selected as the research objects, and they were divided into cerebral watershed infarction group (278 cases) and non cerebral watershed infarction group (122 cases) according to digital subtraction angiography (DSA). All patients were detected by energy spectrum CTA, and the correlation between vascular lesions and collateral compensation were compared. Result: The incidences of ICA severe occlusion, stenosis and multiple intracranial vascular stenosis in the cerebral watershed infarction group were higher than those in non cerebral watershed group, the differences were statistically significant (P<0.05). The incidences of bilateral ICA severe stenosis, ICA occlusion and Willis ring opening in medial watershed infarction group were higher than those in cortical and mixed watershed infarction group (P<0.05); the incidences of unilateral ICA severe stenosis, VBA stenosis and multiple intracranial vascular stenosis in cortical watershed infarction group were higher than those in medial and mixed watershed infarction group (P<0.05). Among 278 patients, 190 cases of Willis loop were open, among which, 66 cases were open only in front traffic, 32 cases were open only in rear traffic, 52 cases were open simultaneously in front and rear traffic, and 40 cases were not open in front and rear traffic. There was no statistical significance in the type of infarction among patients with different Willis circle opening (P>0.05). Among the 278 patients, 120 cases had multiple intracranial vascular stenosis, among which, 34 cases had poor pia mater collateral compensation, and 86 cases had good pia mater collateral compensation. The incidence of cortical watershed infarcts in patients with poor pia mater compensation was higher than that in patients with better compensation, while the incidences of medial and mixed watershed infarcts were lower than those in patients with better compensation (P<0.05). Conclusion: Cerebral watershed infarction is closely related to intracranial and extracranial vascular stenosis and occlusion. The presence of anterior communicating artery can significantly reduce the incidence of medial cerebral watershed infarction; the presence of pia mater compensation in middle cerebral artery lesions can increase the blood supply of affected cortex, and the patients with poor pia mater collateral compensation are prone to lead to cortical cerebral watershed infarction. The specific situation of patients be accurately evaluated by energy spectrum CTA detection, which is helpful to take targeted prevention and treatment measures.
[Key words] Energy spectrum CTA Cerebral watershed infarction Intracranial and extracranial vascular
Stenosis Occlusion Collateral circulation
First-authors address: Foshan Sanshui Peoples Hospital, Foshan 528100, China
doi:10.3969/j.issn.1674-4985.2021.13.036
脑分水岭梗死(cerebral watershed infarction,CWSI)主要是指出现在2条或者多条脑动脉供血边缘地带的脑梗死情况,其中颅内外供血血管闭塞或者狭窄是导致该疾病发生的重要原因,其血管的狭窄程度与CWSI的发生率及严重程度紧密相关[1-2]。据相关研究显示,建立责任血管或者其他部位血管的侧支循环,有利于延缓病情进展,促使患者预后得到显著改善[3]。因此,在对CWSI发病机制探讨的过程中,应充分考虑侧支代偿功能。颈动脉系统不同部位的病变情况能够导致不同类型CWSI产生,同时期侧支循环方式也存在一定差异,但血管病变导致不同类型CWSI侧支循环的具体状况,并且具体与颈动脉系统中的哪支血管病变存在相关性,上述问题在目前的研究中存在一定争议,且对于侧支循环情况的分析也相对较少。……
