SLE继发抗磷脂抗体综合征合并Libman-Sacks心内膜炎一例
2021-01-19卢丽娟黄勤
卢丽娟?黄勤
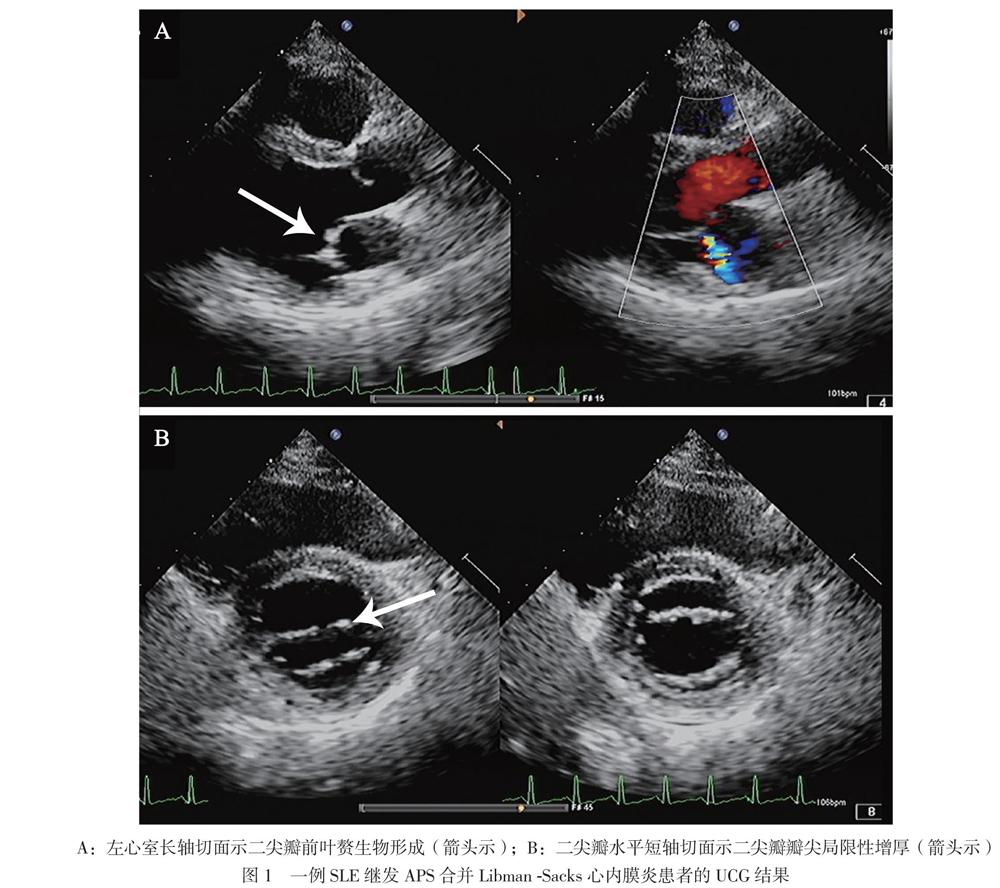
【摘要】临床部分SLE患者可继发抗磷脂抗体综合征(APS),但同时合并非细菌性心内膜炎的患者则较为罕见。该文报道1例SLE继发APS合并Libman-Sacks心内膜炎患者的诊治过程。该患者入院前有发热、关节痛、咽痛和皮疹,入院后UCG示二尖瓣前叶赘生物形成,查狼疮抗体、抗磷脂抗体、狼疮样抗凝物试验阳性,经抗感染治疗后病情未缓解,后患者突发头晕、口周麻木、构音不清、吞咽困难,查头颅MRI见一新发的延髓梗死灶。结合患者临床表现、体征及辅助检查,诊断为APS,Libman-Sacks心内膜炎,延髓梗死,SLE。予免疫抑制、免疫调节、低分子肝素抗凝等治疗后患者病情好转出院。该例的诊治提示,在UCG发现赘生物时,不仅要考虑感染性心内膜炎,同时需要考虑SLE继发APS可能,尤其是对于既往无明确心瓣膜病病史的年轻女性,早期诊断APS合并Libman-Sacks心內膜炎,并给予个体化抗凝治疗,可取得良好疗效。
【关键词】抗磷脂抗体综合征;系统性红斑狼疮;Libman-Sacks心内膜炎;抗凝治疗;
感染性心内膜炎;鉴别诊断
Antiphospholipid antibody syndrome secondary to SLE complicated with Libman-Sacks endocarditis: a case report Lu Lijuan, Huang Qin. Internal Medicine Training Base, Shenzhen Peoples Hospital, Shenzhen 518000, China
【Abstract】In clinical practice, partial patients with systemic lupus erythematosu (SLE) can develop secondary antiphospholipid antibody syndrome (APS), whereas simultaneous complication with non-bacterial endocarditis is rarely encountered. In this article, the diagnosis and treatment of one case of APS secondary to SLE complicated with Libman-Sacks endocarditis were reported. Prior to admission, the patient presented with fever, joint pain, sore throat and rash. UCG upon admission revealed the mass in the anterior leaflet of mitral valve. The patient was tested positive for lupus antibody, antiphospholipid antibody and lupus-like anticoagulant test. The symptoms were not alleviated after anti-infection therapy. Subsequently, the patient suffered from dizziness, numbness around the mouth, unclear articulation and dysphagia. Cranial MRI revealed a new medullary infarction lesion. Combined with clinical manifestations, physical signs and auxiliary examinations, the patient was diagnosed with APS, Libman-Sacks endocarditis, medullary infarction and SLE. After immunosuppression, immunomodulation and low-molecule heparin anticoagulation interventions, the patient was improved and discharged from hospital. The diagnosis and treatment of this case prompted that besides IE, the possibility of APS secondary to SLE should also be considered when UCG revealed a neoplasm, especially for young women who had no clear history of valvular heart diseases. Early diagnosis of APS complicated with Libman-Sacks endocarditis and individualized anticoagulation therapy can yield favorable clinical efficacy.
【Key words】Antiphospholipid antibody syndrome;Systemic lupus erythematosus;
Libman-Sacks endocarditis;Anticoagulation therapy;Infective endocarditis;
Differential diagnosis
抗磷脂抗体综合征(APS)是一种非炎症性自身免疫病,临床上以动脉、静脉血栓形成,病态妊娠(妊娠早期流产和中晚期死胎)和血小板减少等症状为表现,血清中存在抗磷脂抗体,上述症状可以单独或多个共同存在。多见于年轻人,男女发病率之比约为1∶9,女性发病的中位年龄为 30岁[1]。APS可出现在SLE的活动期,而SLE继发APS同时合并Libman-Sacks心内膜炎极为罕见。为提高临床医师对该病的认识水平,现将近年我院收治的一例SLE继发APS合并Libman-Sacks心内膜炎患者的诊治过程综合报告如下。……
